


Overview
Gene therapy treats a disease by delivering genes into a patient's cells, usually a normal copy to take over from a faulty one, through a disarmed virus or a gene-editing tool. It belongs to the wider use of biotechnology in medicine, which also makes human insulin in bacteria, engineers immune cells against cancer, silences genes with RNA and diagnoses disease from its molecules.
Biotechnology in Medicine: Recombinant Therapeutics
Recombinant Therapeutics: Medicines Made by Engineered Cells
Biotechnology entered medicine through recombinant DNA technology, the method of cutting a human gene, joining it to a vector and making a microbe or a cultured cell produce the protein it codes for. Such medicines are called recombinant therapeutics. They can be made in large amounts, and because they are identical to human proteins they do not provoke the unwanted immune reactions caused by the same products taken from animals. They also carry no risk of infection from a non-human source. They belong to a wider class, the biopharmaceuticals or biologics, which are medicines made in, extracted from or partly built from biological sources. In a narrow sense, biopharmaceutical means one made by recombinant DNA technology.
Restriction enzymes, vectors, PCR and gene editing are the tools of recombinant DNA technology. In health they have given hormones made in bacteria, the correction of faulty genes, engineered immune cells, RNA that silences genes, and tests that find disease early.
Genetically Engineered Insulin: Human Insulin from Bacteria
Insulin, the hormone that controls blood sugar, is a peptide made of two short polypeptide chains, chain A and chain B, linked by disulphide bridges. People with diabetes who need insulin once received it from the pancreas of slaughtered cattle and pigs, and some of them developed allergies or other reactions to the foreign protein.
Making human insulin in bacteria had one difficulty. The body first makes insulin as a pro-hormone that carries an extra stretch, the C peptide, which is cut away as the hormone matures, and a bacterium does not do this. In 1983 the American company Eli Lilly solved it by making two DNA sequences, one for chain A and one for chain B, putting each into plasmids of E. coli, producing the two chains separately and joining them by creating disulphide bonds. The result is identical to the insulin of the human body.
Biopharmaceuticals and Biosimilars: India's Biopharma Industry
When the patent on an original biologic expires, other companies may make an officially approved near copy of it. Such a copy is called a biosimilar. It is almost identical to the original product but is made by a different company. Unlike an ordinary generic drug, a biosimilar is a large and complex molecule that is sensitive to small changes in how it is made, which is why it is called similar rather than identical.
India's pharmaceutical industry has moved from a generic-focused model to biopharmaceuticals and biosimilars. India is among the top producers of vaccines in the world and developed the world's first DNA COVID‑19 vaccine, and its bioeconomy grew from US$10 billion in 2014 to US$165.7 billion in 2024. Several programmes drive this activity:
- National Biopharma Mission: Led by the Department of Biotechnology and run by BIRAC, with a budget of US$250 million, half of it from the World Bank, it supports 101 projects in biopharmaceuticals, vaccines, biosimilars, medical devices and diagnostics, and has set up 11 shared facilities for testing and manufacture.
- BIRAC: The Biotechnology Industry Research Assistance Council, set up by the Department of Biotechnology in 2012, funds start-ups through schemes such as the Biotechnology Ignition Grant of up to ₹50 lakh.
- BioE3 Policy: Approved on 24 August 2024, it includes precision biotherapeutics among its sectors, with projects on gene therapy for haemophilia A and gene editing for thalassaemia.
Vaccines and monoclonal antibodies form the other large class of biologics; both act through the immune system.
Gene Therapy: Correcting Faulty Genes
What Is Gene Therapy: Somatic and Germline Gene Therapy
Gene therapy is aimed mainly at inherited disorders, diagnosed in a child or even in an embryo. Viruses, which naturally carry their genes into the cells they infect, are the usual carriers, or vectors, of the new gene, and they are disarmed first so that they cause no disease.
The first clinical gene therapy was given in 1990 to a four-year-old girl with adenosine deaminase (ADA) deficiency. ADA is an enzyme the immune system needs, and the disorder comes from the deletion of its gene. Doctors grew lymphocytes from her blood outside the body, introduced a working ADA gene into them with a retroviral vector and returned them to her. Because lymphocytes do not live for ever, the treatment had to be repeated; a gene put into cells at an early embryonic stage could, in principle, cure the disease for good.
| Type | Cells changed | Is the change inherited? |
|---|---|---|
| Somatic gene therapy | Body cells, not eggs or sperm | No, it affects the patient only |
| Germline gene therapy | Sperm, egg cells or early embryos | Yes, every cell of the child carries it |
Somatic gene therapy is the mainstream of research and treatment. Germline gene therapy would pass the change to future generations, which is why India restricts it. The National Guidelines for Stem Cell Research, 2017, confine the editing of germline cells and human embryos to laboratory studies. In July 2021 the World Health Organization issued the first global recommendations on human genome editing, covering somatic, germline and heritable editing.
Types of Gene Therapy: In Vivo, Ex Vivo and Gene Editing
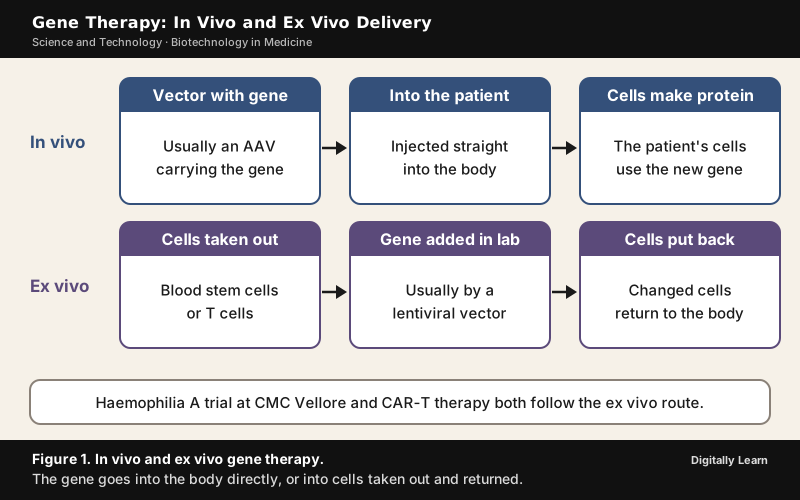
Gene therapy is given in three ways:
- In vivo gene therapy: The vector carrying the gene is put straight into the patient's body. Adeno-associated viruses (AAVs) are the usual vectors here; they cause little immune reaction, enter cells that are dividing and cells that are not, and give long-lasting expression.
- Ex vivo gene therapy: The patient's cells are taken out, changed in the laboratory and put back. Lentiviruses, a kind of retrovirus, are the usual vectors; India's haemophilia trial and CAR‑T therapies work this way.
- Gene editing therapy: Instead of adding a gene, a tool such as CRISPR-Cas9 corrects or switches off the patient's own gene in the cells.
Gene therapy became a licensed medicine slowly. The first approval came in 2003, in China, and many followed. In November 2023 the United Kingdom became the first country to approve Casgevy (exagamglogene autotemcel), a CRISPR-Cas9 gene-edited cell therapy for sickle cell disease and transfusion-dependent beta thalassaemia; the US Food and Drug Administration approved it in December 2023, its first approval of a CRISPR-based therapy.
Gene Therapy for Sickle Cell Disease and Haemophilia in India
India carries a large burden of inherited disease, the main target of gene therapy. Some 70 million people in India suffer from rare diseases, 80 per cent of them genetic. Haemophilia is an inherited bleeding disorder in which a shortage of the clotting protein Factor VIII or Factor IX stops the blood from clotting, and India has the second largest burden of it in the world, about 1,36,000 cases.
- Haemophilia A trial: At the Centre for Stem Cell Research, CMC Vellore, a unit of BRIC-inStem supported by the Department of Biotechnology, five patients received their own blood stem cells carrying a Factor VIII gene delivered by a lentiviral vector. The yearly bleeding rate fell to zero in all five over a combined follow-up of 81 months, removing the need for repeated infusions of the clotting factor; the results were published in the New England Journal of Medicine.
- BIRSA 101 for sickle cell disease: Launched on 19 November 2025 by CSIR‑IGIB, it is India's first indigenous CRISPR-based gene therapy. Sickle cell disease weighs most on tribal communities of central and eastern India, and the therapy, transferred to the Serum Institute of India, is meant to cost a fraction of the ₹20 crore to ₹25 crore that such treatment costs abroad.
- Rules for trials: Gene therapy products follow the National Guidelines for Gene Therapy Product Development and Clinical Trials, 2019, issued by the ICMR, CDSCO and DBT; trials need an Institutional Ethics Committee, and marketing approval comes from the CDSCO under the New Drugs and Clinical Trials Rules, 2019.
Cell, RNA and Mitochondrial Therapies
CAR‑T Cell Therapy and NexCAR19
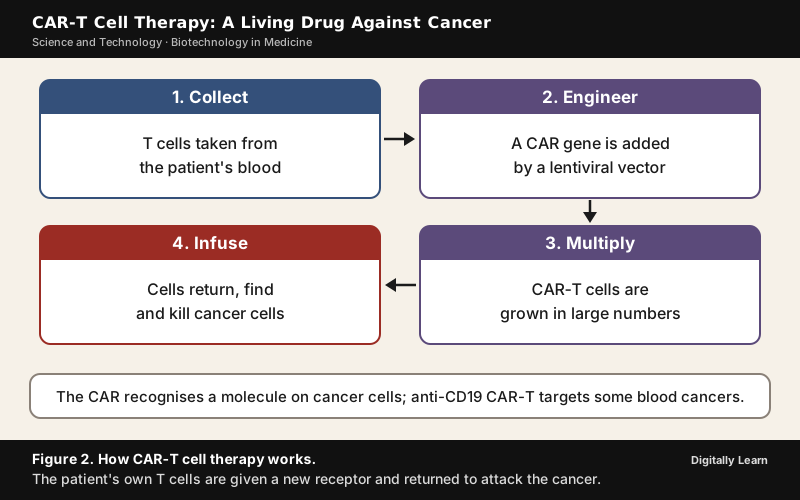
CAR‑T cell therapy turns a patient's own immune cells into a cancer treatment. T cells are taken from the patient's blood and given a gene, usually through a lentiviral vector, for a chimeric antigen receptor (CAR), a receptor that recognises a chosen molecule on the surface of cancer cells. Infused back into the patient, the cells multiply and attack the tumour, acting as a "living drug".
- First in India: On 4 June 2021 the first CAR‑T cell therapy in India was given at ACTREC, Tata Memorial Centre, Mumbai, with cells designed and made at IIT Bombay.
- NexCAR19: Launched by the President on 4 April 2024, it is India's first indigenous CAR‑T therapy, developed by IIT Bombay and Tata Memorial Centre with the company ImmunoACT, and described as the world's most affordable CAR‑T therapy.
- Cost of CAR‑T therapy: Imported CAR‑T therapy cost ₹3 crore to ₹4 crore per patient, mainly because it is complex to make.
- Indian products: BIRAC supported the development and trials of two anti-CD19 CAR‑T products, NexCAR19 and Qartemi, which are now in use for some blood cancers.
RNA Interference: Gene Silencing Therapies
RNA interference (RNAi) is a natural process in all eukaryotes in which a double-stranded RNA binds to a matching messenger RNA and stops it from being translated, so the gene is silenced. It is a cell's defence against viruses with RNA genomes and against mobile genetic elements. Andrew Fire and Craig Mello, who described it in the nematode Caenorhabditis elegans in 1998, shared the Nobel Prize in Physiology or Medicine in 2006.
- Gene silencing medicines: Small interfering RNAs (siRNAs) are designed to switch off a disease-causing gene. Patisiran, approved in 2018, was the first; by 2025 seven such medicines had been approved, all for diseases that start in the liver.
- Cancer research: Tumour-suppressing microRNAs lost in cancer cells are being put back, and in laboratory models they have shown activity against tumours and made resistant cancer cells sensitive to treatment again.
- Crop protection: Tobacco plants given a nematode gene that produces both sense and antisense RNA silence the parasite's own gene and are protected from it. Transgenic papaya carrying a gene fragment of papaya ringspot virus resists the virus, a protection that probably works through RNAi.
Mitochondrial Replacement Therapy: Three-Parent Babies
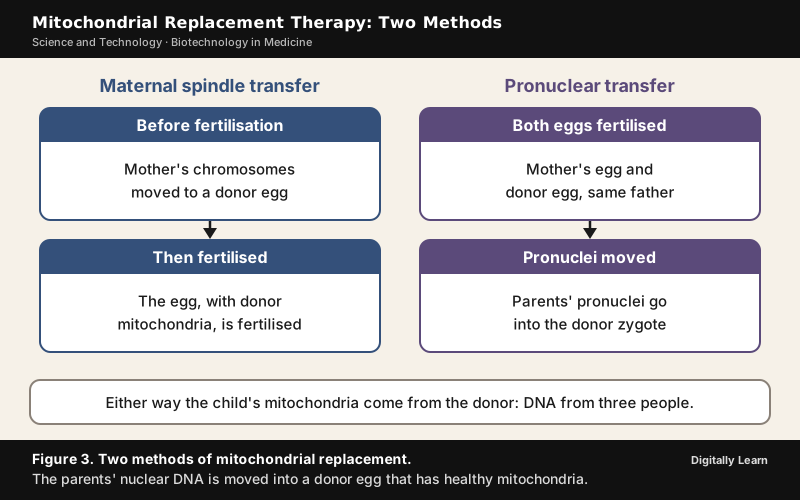
Mitochondria carry a small genome of their own, and a child inherits its mitochondria from the mother only. An egg carries about 2,00,000 copies of mitochondrial DNA, and the mitochondria of the sperm are usually destroyed after fertilisation. A mother with faulty mitochondria can therefore pass a mitochondrial disease to every child. Mitochondrial replacement therapy (MRT) prevents this by giving the embryo healthy mitochondria from a donor egg, so that the child has DNA from three people.
- Maternal spindle transfer: Before fertilisation, the chromosomes of the mother's egg are moved into a donor egg whose own nucleus has been removed; the egg is then fertilised.
- Pronuclear transfer: After fertilisation, the two pronuclei of the mother's fertilised egg are moved into a fertilised donor egg whose own pronuclei have been removed.
- Where it is allowed: The United Kingdom approved these two methods in 2015, and eight babies had been born there through MRT by July 2025; Australia also permits it.
Molecular Diagnostics and Precision Medicine
Molecular Diagnostics: PCR, RT‑PCR, Probes and ELISA
Molecular diagnosis finds a disease from its molecules, such as the genes of a pathogen, a mutation, or the antigens and antibodies in the blood. Conventional tests of serum and urine find an infection only after the pathogen has multiplied enough to cause symptoms, whereas molecular methods work at far lower amounts and so allow diagnosis before symptoms appear. Four methods are in common use:
- Polymerase chain reaction (PCR): It amplifies the nucleic acid of a bacterium or virus present in very low concentration. It is used routinely to detect HIV in suspected AIDS patients and to detect gene mutations in suspected cancer patients.
- Reverse transcription PCR (RT‑PCR): Reverse transcription first turns RNA into complementary DNA, which PCR then amplifies, so it measures a specific RNA; this is how RNA viruses are detected.
- Probes: A single-stranded DNA or RNA tagged with a radioactive molecule pairs with its matching DNA and is detected by autoradiography; a mutated gene does not pair with the probe and so does not show up.
- Enzyme-linked immunosorbent assay (ELISA): It works on the antigen-antibody reaction. It finds an infection either from the pathogen's antigens or from the antibodies the body has made against it.
Transgenic Animals in Medicine and Drug Testing
Transgenic animals are animals whose DNA has been changed to carry and express an extra, foreign gene. Rats, rabbits, pigs, sheep, cows and fish have been made transgenic, but over 95 per cent of all transgenic animals are mice. They serve medicine in five ways:
- Normal physiology: They show how genes are regulated and how they shape growth, for example through the insulin-like growth factor.
- Models of disease: Transgenic models exist for cancer, cystic fibrosis, rheumatoid arthritis and Alzheimer's, so new treatments can be tested on them.
- Biological products: Animals can be made to produce human proteins, such as alpha‑1-antitrypsin, used to treat emphysema. In 1997 the first transgenic cow, Rosie, gave milk containing human alpha-lactalbumin, 2.4 grams per litre, which is nutritionally more balanced for human babies than ordinary cow milk.
- Vaccine safety: Transgenic mice are being used to test the safety of polio vaccine batches, which could replace the use of monkeys.
- Chemical safety: Animals made more sensitive to toxic substances give toxicity results in less time.
Precision Medicine: Pharmacogenomics and Genome India
Pharmacogenomics studies how a person's genes affect the way they respond to medicines, so that a drug and its dose can be chosen for the individual's genetic make-up. People with G6PD deficiency, for example, are at higher risk of their red blood cells breaking down when given certain drugs.
Precision medicine of this kind needs a reference of the population's own genetic variation. The Genome India project sequenced the whole genomes of 10,074 healthy Indians from 83 populations, and the data, kept at the Indian Biological Data Centre, is meant for developing Indian genetic chips, diagnostic tests and therapies.
Previous Year UPSC‑CSE Questions
Each Prelims question is explained option by option, and each Mains question comes with an answer outline.
- UPSC Prelims 2021In the context of hereditary diseases, consider the following statements:
- Passing on mitochondrial diseases from parent to child can be prevented by mitochondrial replacement therapy either before or after in vitro fertilization of egg.
- A child inherits mitochondrial diseases entirely from mother and not from father.
Which of the statements given above is/are correct?
How to approach this Prelims question
Approach: Both statements turn on how mitochondria pass from parent to child and how replacement therapy swaps them.
- Statement 1: MRT gives the embryo a donor's healthy mitochondria, either before fertilisation (maternal spindle transfer) or after it (pronuclear transfer), so the disease is not passed on. True.
- Statement 2: The egg brings about 2,00,000 copies of mitochondrial DNA and the sperm's mitochondria are destroyed after fertilisation, so mitochondrial diseases come from the mother. True.
Trap to watch: The words 'before or after' in statement 1 look like a trick, but both hold, since maternal spindle transfer works on the unfertilised egg and pronuclear transfer on the fertilised egg.
Why each option is right or wrong:
- (a) 1 only: Wrong. Statement 2 is also true, because mitochondria come from the mother.
- (b) 2 only: Wrong. MRT can be done before or after fertilisation.
- (c) Both 1 and 2: Correct. MRT prevents transmission, and the disease is inherited from the mother.
- (d) Neither 1 nor 2: Wrong. Both statements are true.
Answer: (c) Both 1 and 2. Mitochondria come only from the mother, and MRT can replace them before or after fertilisation.
- UPSC Prelims 2020In the context of recent advances in human reproductive technology, "Pronuclear Transfer" is used for
How to approach this Prelims question
Approach: In pronuclear transfer, the mother's egg and a donor egg are both fertilised, and the parents' pronuclei are moved into the donor zygote whose own pronuclei have been removed. The child keeps the parents' nuclear DNA but gets the donor's healthy mitochondria, which prevents mitochondrial disease.
Trap to watch: Option (a) tempts because the method uses IVF, but the fertilisation is ordinary IVF with the father's sperm; what is transferred is the pronuclei.
Why each option is right or wrong:
- (a) fertilization of egg in vitro by the donor sperm: Wrong. Both eggs are fertilised with the father's sperm, not a donor's.
- (b) genetic modification of sperm producing cells: Wrong. No gene is changed; nuclei are moved between zygotes.
- (c) development of stem cells into functional embryos: Wrong. The method starts from fertilised eggs, not stem cells.
- (d) prevention of mitochondrial diseases in offspring: Correct. The child gets the donor's healthy mitochondria.
Answer: (d) prevention of mitochondrial diseases in offspring. The child keeps the parents' nuclear DNA but receives a donor's healthy mitochondria.
- UPSC Prelims 2019'RNA interference (RNAi)' technology has gained popularity in the last few years. Why?
- It is used in developing gene silencing therapies.
- It can be used in developing therapies for the treatment of cancer.
- It can be used to develop hormone replacement therapies.
- It can be used to produce crop plants that are resistant to viral pathogens.
Select the correct answer using the code given below.
How to approach this Prelims question
Approach: RNAi switches a gene off by destroying its messenger RNA, so each use is tested against that one action.
- Statement 1: Gene silencing therapies, such as the siRNA medicine patisiran, are its most direct use. True.
- Statement 2: MicroRNAs lost in cancer cells are being restored to fight tumours. True.
- Statement 3: A hormone replacement supplies a missing hormone, and silencing a gene cannot add one. False.
- Statement 4: Crops carrying a viral gene fragment resist the virus, a protection that probably works through RNAi. True.
Trap to watch: Statement 3 sounds like one more therapy, but RNAi only takes a gene's product away and cannot supply a missing hormone.
Why each option is right or wrong:
- (a) 1, 2 and 4: Correct. RNAi gives gene silencing medicines, cancer treatments and virus-resistant crops.
- (b) 2 and 3: Wrong. Statement 3 is false, and statements 1 and 4 are true.
- (c) 1 and 3: Wrong. RNAi cannot replace a missing hormone.
- (d) 1 and 4 only: Wrong. RNAi is also being developed against cancer.
Answer: (a) 1, 2 and 4. RNAi silences genes, which serves medicine, cancer research and crop protection but cannot supply a hormone.
- UPSC Prelims 2004The hormone insulin is a
How to approach this Prelims question
Approach: Insulin is built of two short polypeptide chains linked by disulphide bridges. That makes it a peptide hormone, which is also why bacteria can be engineered to make its chains.
Trap to watch: Students who take every hormone to be a sterol pick option (d), but insulin's two polypeptide chains make it a peptide hormone.
Why each option is right or wrong:
- (a) Glycolipid: Wrong. Insulin is made of polypeptide chains, not a glycolipid.
- (b) Fatty acid: Wrong. Insulin is made of polypeptide chains, not a fatty acid.
- (c) Peptide: Correct. Insulin is two polypeptide chains joined by disulphide bridges.
- (d) Sterol: Wrong. Insulin is made of polypeptide chains, not a sterol.
Answer: (c) Peptide. Insulin is two polypeptide chains joined by disulphide bridges.
- UPSC Prelims 1998Haemophilia is a genetic disorder which leads to
How to approach this Prelims question
Approach: Haemophilia is caused by a shortage of the clotting proteins Factor VIII or Factor IX. Without them the blood does not clot, so bleeding goes on; this is why gene therapy aims to make the body produce Factor VIII itself.
Trap to watch: 'Haemo' in haemophilia means blood, which draws students to option (a), but the disorder concerns clotting factors, not haemoglobin.
Why each option is right or wrong:
- (a) decrease in haemoglobin level: Wrong. Haemophilia is a shortage of clotting factors, not of haemoglobin.
- (b) rheumatic heart disease: Wrong. Haemophilia is a bleeding disorder, not a disease of the heart.
- (c) decrease in WBC: Wrong. Haemophilia affects clotting factors, not white cells.
- (d) non-clotting of blood: Correct. A missing clotting factor stops the blood from clotting.
Answer: (d) non-clotting of blood. A missing clotting factor, Factor VIII or Factor IX, stops the blood from clotting.
- UPSC Mains 2018 GS‑IIIWhy is there so much activity in the field of biotechnology in our country? How has this activity benefitted the field of biopharma?
Answer outline
The outline sets out what the question asks, the main arguments, relevant examples and the direction of the conclusion; it is not a full model answer.
Introduction: Biotechnology makes medicines in living cells, and India's bioeconomy grew from US$10 billion in 2014 to US$165.7 billion in 2024.
Body (sub-themes to develop):
- Why the activity: The Department of Biotechnology since 1986; BIRAC since 2012 and its grants; the National Biopharma Mission with the World Bank; the BioE3 Policy of 2024; a large drug and vaccine manufacturing base.
- Gains for biopharma: A move from generics to biopharmaceuticals and biosimilars; India among the top vaccine producers and maker of the first DNA COVID‑19 vaccine; 11 shared facilities for testing and manufacture.
- New frontiers: NexCAR19, the CMC Vellore haemophilia A gene therapy and BIRSA 101, with recombinant insulin as the model product.
Conclusion: Low-cost manufacture of complex biologics is where India's advantage lies, provided regulation and quality keep pace.
Sources
- NCERT: Biology (Class XII), Biotechnology: Principles and Processes
- NCERT: Biology (Class XII), Biotechnology and its Applications
- PIB: First CAR‑T cell therapy at ACTREC, Tata Memorial Centre (8 June 2021)
- PIB: India's first home-grown CAR‑T cell therapy (4 April 2024)
- PIB: First-in-human gene therapy for haemophilia A (11 December 2024)
- PIB: BIRSA 101, India's first indigenous CRISPR-based gene therapy (19 November 2025)
- PIB: PM‑STIAC meeting on cell and gene therapy (21 January 2025)
- PIB: Parliament question, self-reliance in CRISPR and gene editing (19 March 2026)
- PIB: The rise of India's bioeconomy (27 March 2025)
- PIB: Parliament question, Indian Biological Data Centre (19 March 2025)
- ICMR and DBT: National Guidelines for Stem Cell Research, 2017
- WHO: Recommendations on human genome editing (12 July 2021)
- Wikipedia: Gene therapy
- Wikipedia: CAR T cell
- Wikipedia: RNA interference
- Wikipedia: Mitochondrial replacement therapy
- Wikipedia: Mitochondrial DNA
- Wikipedia: Biosimilar
- Wikipedia: Biopharmaceutical
- Wikipedia: Adeno-associated virus
- Wikipedia: Exagamglogene autotemcel
- Wikipedia: Pharmacogenomics
- Wikipedia: Reverse transcription polymerase chain reaction
- Wikipedia: Papaya ringspot virus
- Wikipedia: ELISA
- UPSC: Civil Services Examination question papers
Editorial Disclaimer
This article draws on the NCERT Biology textbook for Class XII and on the official and scientific sources in the Sources list.


