


Overview
West Bengal joins PM-JAY
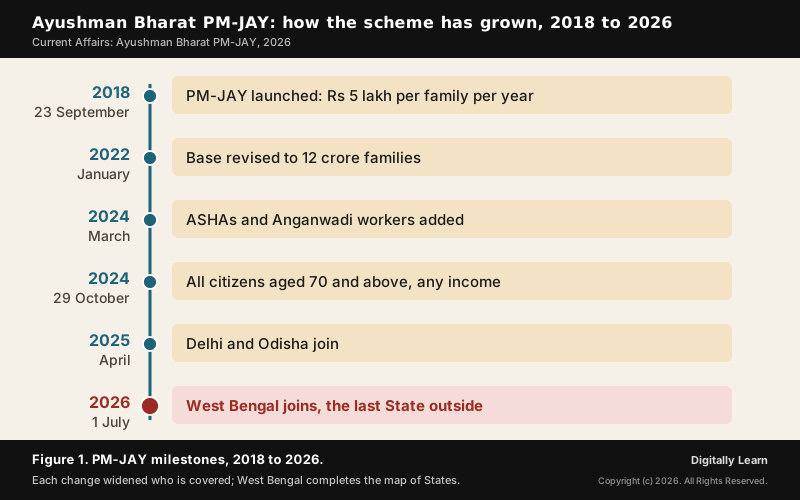
The Ayushman Bharat Yojana is India's flagship health programme, with two pillars: Ayushman Arogya Mandirs for primary care and the Pradhan Mantri Jan Arogya Yojana (PM-JAY), which gives about 12 crore poor and vulnerable families, and every citizen aged 70 and above, cashless hospital care of up to Rs 5 lakh a year. West Bengal, the last State outside PM-JAY, decided in May 2026 to join from 1 July 2026.
Ayushman Bharat West Bengal: Why PM-JAY Is in the News in 2026
West Bengal Joins Ayushman Bharat PM-JAY from 1 July 2026
The decision came from West Bengal's new government. At its first Cabinet meeting after the 2026 Assembly election, Chief Minister Suvendu Adhikari's government decided to implement the Ayushman Bharat Yojana, and he said the process had begun to put major Central schemes, PM-JAY among them, into effect in the State. The previous government had opted out of PM-JAY in favour of its own health insurance scheme, Swasthya Sathi.
On 23 May 2026 Adhikari and Union Health Minister J.P. Nadda met by video call. Adhikari announced that enrolment for Ayushman cards had begun and that benefits would be available from 1 July. The nearly six crore people holding Swasthya Sathi cards would be moved to Ayushman Bharat. The Union Health Ministry also conveyed a National Health Mission resource envelope of Rs 3,505.59 crore for 2026-27 to the State and released a first sanction of Rs 527.58 crore.
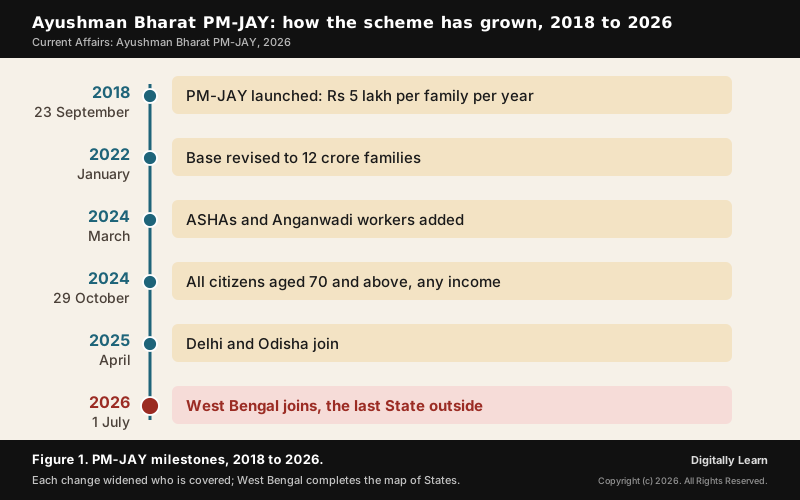
West Bengal was the last of three holdouts. In September 2024 the scheme ran in 33 States and Union Territories, all except Delhi, West Bengal and Odisha. Delhi and Odisha joined in April 2025 after new governments took office there, and West Bengal's turn came in 2026.
Health Survey 2025 and National Health Accounts: What the New Data Show
Two sets of data in May 2026 measured how far India has come. The first is the Survey on Health of the 80th round of the National Sample Survey, the first such survey since the pandemic and since PM-JAY matured. It found that health insurance coverage has grown about threefold since PM-JAY began in 2018. Yet the hospitalisation rate has not recovered to its 2014 level, so an insurance card does not by itself guarantee a hospital bed.
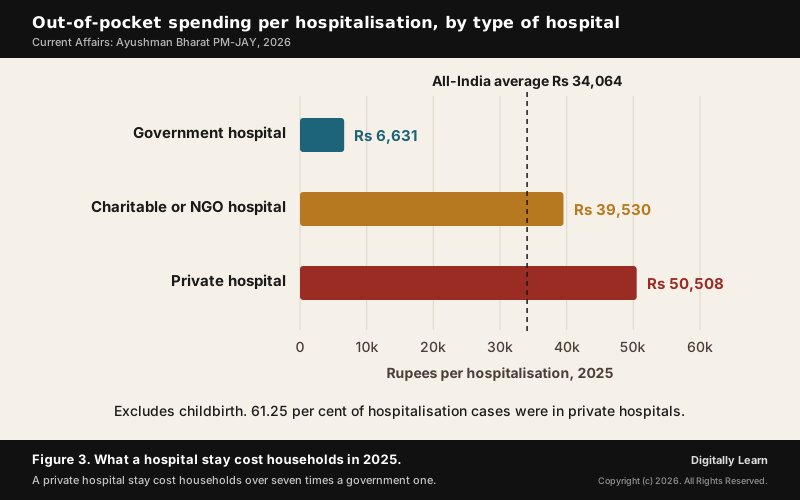
- Cost of a hospital stay: In 2025 the average out-of-pocket spending per hospitalisation, excluding childbirth, was Rs 34,064: Rs 31,484 in rural areas and Rs 38,688 in urban areas.
- Public against private: Rs 6,631 in a government hospital, Rs 39,530 in a charitable or NGO hospital and Rs 50,508 in a private one; 61.25 per cent of hospitalisation cases were in private hospitals.
- Who has cover: As of 2025, 47.4 per cent of rural and 44.3 per cent of urban households had some kind of health cover.
- Childbirth: Over 95 per cent of births now take place in institutions, and 98 per cent of women reported antenatal care; a delivery in a private facility cost Rs 37,630 on average against Rs 2,299 in a public one.
The second is the National Health Accounts estimates for 2022-23. Out-of-pocket expenditure, the money households pay at the point of care from their own pockets, fell to 43.4 per cent of total health expenditure in 2022-23, from 64.2 per cent in 2013-14. In 2021-22 it had dipped to 39.4 per cent, because the government's one-time pandemic spending raised its share that year. The Health Ministry credits the long fall to the Ayushman Arogya Mandirs; the full figures are explained on the page on the National Health Accounts estimates 2022-23.
What Is Ayushman Bharat: Two Pillars of Universal Health Coverage
Ayushman Bharat Arogya Mandir: The Primary Care Pillar
Ayushman Bharat is the Government of India's flagship health programme. It grew out of the National Health Policy 2017 and rests on two pillars that work at different levels of the health system: Ayushman Arogya Mandirs for care close to home, and PM-JAY for hospital care. A third programme, the Ayushman Bharat Digital Mission, launched on 27 September 2021, builds the digital health records that link them.
The Ayushman Arogya Mandirs, formerly called Health and Wellness Centres, are sub-centres and primary health centres upgraded to give comprehensive primary health care, with free medicines and diagnostics. More than 1.8 lakh of them are operational across the country, and the Health Ministry credits them with much of the fall in out-of-pocket spending. In Delhi the government has been setting them up since May 2025: 45 opened in Shakarpur in July 2026 took the city past 415, against a target of 1,100.
Both pillars serve one goal. Universal health coverage means that all people can use the full range of quality health services they need, when and where they need them, without financial hardship. It is one of the targets of the Sustainable Development Goals adopted in 2015, and in 2019 the UN General Assembly's high-level meeting on it reaffirmed that health is a precondition for, and an outcome of, sustainable development.
The primary-care pillar is also where critics see the biggest gap. The network of Arogya Mandirs, which gives free medicines and diagnostics, is still underfunded for the job of managing chronic diseases, a field the private sector dominates. Critics also point out that the existing sub-centres, primary health centres and community health centres were given a common "Health and Wellness Centre" prefix, which blurred their separate mandates and shifted the focus from the health of the population to individual well-being.
Ayushman Bharat Pradhan Mantri Jan Arogya Yojana: Launch and Design
The Pradhan Mantri Jan Arogya Yojana (PM-JAY) was launched on 23 September 2018. It is the world's largest health assurance scheme fully financed by government. Each entitled family gets a cover of Rs 5 lakh a year for secondary and tertiary care hospitalisation in empanelled public and private hospitals anywhere in India. Health assurance here means the government pays for the treatment, so the family pays nothing at the hospital.
- Cashless and portable: Treatment is free at the point of care, and a beneficiary can use any empanelled hospital in the country, not only in the home State.
- Whole family: All members of an eligible family are covered, irrespective of age.
- Health Benefit Package: A revised package of 1,961 procedures, with free drugs, diagnostics up to 3 days before admission and 15 days of post-discharge medication, food and lodging.
- Entitlement-based: Eligibility comes from a database, not from an application or a premium paid by the family.
When PM-JAY began, many States were running the centrally sponsored Rashtriya Swasthya Bima Yojana, and some had their own health insurance schemes. PM-JAY was designed to run alongside those schemes and build on their strengths, in a spirit of cooperative federalism.
Ayushman Card Eligibility and Benefits: Who Is Covered and for What
Ayushman Card Eligibility: SECC 2011, 12 Crore Families and Additions
Who gets an Ayushman card was first decided from the Socio-Economic Caste Census (SECC) of 2011. In rural areas families qualified on six deprivation criteria, and in urban areas on eleven occupational criteria. In 2021 that gave about 10.73 crore eligible families, roughly 50 crore people.
- January 2022: Using a decadal growth rate of 11.7 per cent, the Centre revised the beneficiary base to 12 crore families and let States use other databases of similar profile to verify families the SECC list could not identify.
- State additions: Many States and Union Territories have widened coverage beyond the Central list at their own cost.
- March 2024: 37 lakh Accredited Social Health Activists (ASHAs), Anganwadi Workers, Anganwadi Helpers and their families were added.
- October 2024: All citizens aged 70 and above, whatever their income.
The base today is about 12 crore families, roughly 55 crore people. Because eligibility rests on lists, a family that is poor but missing from them falls outside, while a family that is not poor enough for the lists but cannot afford private insurance is left with no cover at all. That group is called the missing middle.
Ayushman Card for Senior Citizens: Cover for 70 and Above
On 11 September 2024 the Union Cabinet extended PM-JAY to all senior citizens aged 70 and above, irrespective of their socio-economic status, and the cover began on 29 October 2024. It was meant to reach about 6 crore senior citizens in 4.5 crore families, each of whom gets a new distinct card, known as the Ayushman Vay Vandana card.
- In a family already covered: The senior gets an additional top-up of up to Rs 5 lakh a year for personal use, not shared with younger family members.
- In any other family: A cover of up to Rs 5 lakh a year on a family basis.
- Other public schemes: Those in the Central Government Health Scheme, the Ex-Servicemen Contributory Health Scheme or Ayushman CAPF can keep that scheme or choose PM-JAY; those with private insurance or under the Employees’ State Insurance scheme remain eligible.
| Who | What PM-JAY gives |
|---|---|
| Family on the SECC or State list | Up to Rs 5 lakh a year for the whole family, any age |
| Person aged 70 or above in a covered family | The family cover, plus a personal top-up of up to Rs 5 lakh a year |
| Person aged 70 or above in any other family | Up to Rs 5 lakh a year on a family basis |
| Person aged 70 or above in CGHS, ECHS or Ayushman CAPF | A choice: keep that scheme or move to PM-JAY |
| ASHA, Anganwadi Worker or Helper | Covered with the family since March 2024 |
Delhi, which joined the scheme in 2025, shows the senior cover at work: of the 7.72 lakh Ayushman cards issued there by May 2026, 2.9 lakh were under the Vay Vandana scheme.
Ayushman Card Benefits in Numbers: Cards, Admissions and Hospitals
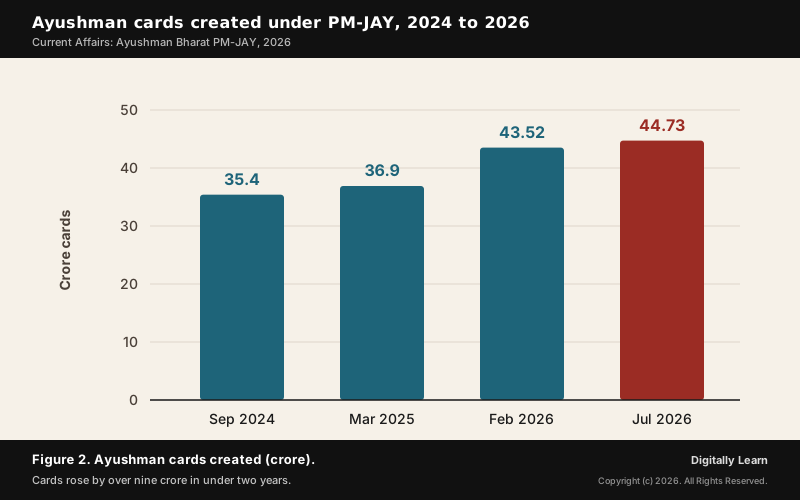
Use of the scheme has climbed steadily. In July 2026 Parliament was told that more than 44.73 crore Ayushman cards had been created and over 12.69 crore hospital admissions, worth Rs 1.92 lakh crore, authorised under PM-JAY. In September 2024 the figures were 35.4 crore cards and 7.79 crore admissions.
- Women: 49 per cent of Ayushman cards had gone to women by September 2024, and women accounted for 3.61 crore hospital admissions.
- Portability: By September 2024, 11.9 lakh hospitalisations worth Rs 3,100 crore had been authorised in a State other than the patient’s own.
- Hospitals: The number of empanelled hospitals had risen to 36,229 by 28 February 2026.
States can also build on the Central cover. Rajasthan has merged its own MAA Yojana with PM-JAY and activated inter-State portability in 2026, so its eligible families, 1.36 crore of them, can be treated in government and private hospitals across the country.
How PM-JAY Works: Funding, the National Health Authority and the States
Centre-State Funding, the National Health Authority and Empanelment
PM-JAY is a centrally sponsored scheme: the Centre and the States share its cost. The premium is shared 60:40 between the Centre and the States, except in the North Eastern States and the three Himalayan States, where the ratio is 90:10. The Centre pays 100 per cent for Union Territories without a legislature, and 60:40 applies to those with one.
- National Health Authority (NHA): Set up by the Health Ministry to administer the scheme, which comes with a national IT platform and data analytics to detect fraud and abuse.
- State Health Agencies: Run the scheme in each State, with District Implementation Units that visit empanelled hospitals to understand the problems of patients and hospitals.
- Empanelment: Every government hospital with in-patient services is deemed empanelled, and public hospitals are paid at the same rates as private ones; private hospitals join through the NHA’s Hospital Engagement Module.
- Grievances: A three-tier system at district, State and national level, a national call centre (14555) for beneficiaries and a separate one (14413) for hospitals.
The States carry the scheme on the ground, which is why their cooperation matters. When the Centre and a State disagree, families in that State lose the cover, as West Bengal's Chief Minister said had happened there under the previous government.
Health as a State Subject: Why States Opted Out and Came Back
Health is a State subject. Entry 6 of the State List in the Seventh Schedule of the Constitution reads "public health and sanitation; hospitals and dispensaries", so the States organise health services, and a centrally sponsored scheme needs their agreement to run. States with schemes of their own sometimes preferred them, as Delhi, Odisha and West Bengal did for years. Public health sits in the State List alongside agriculture, police and local government, while subjects such as defence and railways are in the Union List. The duty itself runs through every level of government: under Article 47, a Directive Principle, the State shall regard the improvement of public health as among its primary duties.
The money question has not gone away either. In September 2026 private hospitals in Haryana stopped filing Ayushman claims in protest at about Rs 1,200 crore of dues unpaid since January, and the Indian Medical Association warned of a complete withdrawal of services from 16 September. The State's officials said services continued normally and invited the doctors for talks.
Impact and Challenges of Ayushman Bharat: Costs, Fraud and Access
Financial Protection: What Ayushman Bharat Has Improved
- Savings for families: Government estimates put the savings on out-of-pocket spending at over Rs 1.25 lakh crore, and say that without PM-JAY the total cost of the treatments it paid for would have been 1.5 to 2 times higher.
- Poverty prevented: The government estimates that the scheme helps keep over six crore Indians a year from falling into poverty because of health spending.
- Lower out-of-pocket share: From 64.2 per cent of total health expenditure in 2013-14 to 43.4 per cent in 2022-23.
- Wider cover: Insurance coverage about three times what it was before 2018, with the public sector absorbing the cost of much primary and secondary care.
- Cheaper typical care: The median out-of-pocket cost fell to Rs 11,285 per hospitalisation, and public outpatient care costs households almost nothing.
Challenges: Package Rates, Unpaid Dues, Fraud and the Missing Middle
The scheme's weak spots show up where money changes hands. PM-JAY and the State schemes often reimburse hospitals below market rates, so private hospitals recover the difference by billing patients separately for diagnostics and other services. The poor have nominal cover but are often shut out of its benefits in practice, while the insured middle class faces rising catastrophic costs.
- Claims and payments: Rejection of claims for incorrect documents, long delays in reimbursement and dependence on digital services, as the Haryana dues dispute of 2026 showed.
- Fraud: In June 2026 Jammu and Kashmir suspended a doctor and ordered an inquiry into the alleged misrepresentation of 103 cardiac procedures under PMJAY-SEHAT at the Government Medical College, Anantnag.
- What is not covered: Most insurance covers only hospitalisation, so outpatient care and medicines are still paid from the pocket; specialists have suggested extending outpatient mental health benefits under PM-JAY.
- Small share of spending: Government-financed health insurance schemes together spent Rs 26,266 crore in 2022-23, about 3 per cent of total health expenditure, while private hospitals took the largest share of current health expenditure, 30.83 per cent.
The direction of reform follows from this. Having shielded families from poverty and achieved near-universal institutional delivery, the next phase needs stronger public hospitals that can compete with the private sector for tertiary care, better-funded primary care to manage chronic disease, and package rates that private hospitals accept without passing costs to patients.
Ayushman Bharat UPSC Relevance: Syllabus Links and Exam Angles
Ayushman Bharat in the UPSC Syllabus: GS Paper II and Prelims
- GS Paper II: Issues relating to the development and management of the health sector; welfare schemes for vulnerable sections and their performance; Centre-State relations in a State subject (see the GS Paper II syllabus).
- GS Paper III: Inclusive growth and government budgeting, through out-of-pocket spending and health financing.
- Prelims: The two pillars, the cover, eligibility, the 70-plus extension, funding ratios and the State List entry.
- Essay: Health care and the welfare State; primary health care and development.
Previous Year UPSC-CSE Questions By the end you will be able to draft model answers for the following UPSC questions. Each question carries a collapsible framework showing how to approach it in the exam.
- UPSC Mains 2024 GS-IIIn a crucial domain like the public healthcare system the Indian State should play a vital role to contain the adverse impact of marketisation of the system. Suggest some measures through which the State can enhance the reach of public healthcare at the grassroots level.
Answer outline: how to structure the answer
What the question asks, the main arguments, relevant examples and the direction of the conclusion. This is not a full model answer.
Introduction: Introduce the gap: in 2025 a private hospital stay cost a household Rs 50,508 against Rs 6,631 in a government hospital, and 61.25 per cent of hospitalisations were private.
Body (sub-themes to develop):
- Adverse impact of marketisation: package rates below market lead to separate billing; insured but excluded poor; catastrophic costs for the middle class.
- Primary care: fund the Ayushman Arogya Mandirs (over 1.8 lakh) for free medicines, diagnostics and chronic disease care.
- Public hospitals: deemed empanelment and equal reimbursement under PM-JAY; build tertiary capacity to compete with private hospitals.
- Regulation: rate setting and fraud control through the National Health Authority; grievance system.
- Coverage gaps: outpatient and medicines; the missing middle.
Conclusion: Conclude that the State reaches the grassroots best by strengthening its own primary and secondary care, using insurance to protect families rather than to replace public provision.
- UPSC Mains 2015 GS-IIPublic health system has limitations in providing universal health coverage. Do you think that the private sector could help in bridging the gap? What other viable alternatives would you suggest?
Answer outline: how to structure the answer
What the question asks, the main arguments, relevant examples and the direction of the conclusion. This is not a full model answer.
Introduction: Introduce universal health coverage as care without financial hardship, and note that out-of-pocket spending was still 43.4 per cent of total health expenditure in 2022-23.
Body (sub-themes to develop):
- Limits: State capacity, curative focus, underfunded primary care, health a State subject.
- Private sector can help: PM-JAY's empanelled private hospitals and portability widen access.
- But: package rates and separate billing, fraud cases, high private costs.
- Alternatives: Arogya Mandirs; stronger public hospitals; State schemes integrated with PM-JAY; outpatient cover; regulation.
Conclusion: Conclude that the private sector can fill gaps under public rules and prices, but universal coverage rests on a strong public base.
- UPSC Mains 2020 GS-IIIn order to enhance the prospects of social development, sound and adequate health care policies are needed particularly in the fields of geriatric and maternal health care. Discuss.
Answer outline: how to structure the answer
What the question asks, the main arguments, relevant examples and the direction of the conclusion. This is not a full model answer.
Introduction: Introduce health policy as a lever of social development, with the elderly and mothers the two groups most exposed to health costs.
Body (sub-themes to develop):
- Geriatric care: PM-JAY for all aged 70 and above, about 6 crore seniors; top-up of Rs 5 lakh in covered families; choice for CGHS and ECHS members.
- Maternal care: over 95 per cent institutional births and 98 per cent antenatal care.
- Gaps: private deliveries cost over 16 times public ones; outpatient and medicines not covered for the elderly; chronic disease care in primary centres underfunded.
Conclusion: Conclude that cover is now near-universal for these groups, and the next task is affordable outpatient, chronic and public maternity care.
- UPSC Mains 2021 GS-II“Besides being a moral imperative of a Welfare State, primary health structure is a necessary precondition for sustainable development.” Analyze.
Answer outline: how to structure the answer
What the question asks, the main arguments, relevant examples and the direction of the conclusion. This is not a full model answer.
Introduction: Introduce primary health care as the first contact of citizens with the health system, the first pillar of Ayushman Bharat.
Body (sub-themes to develop):
- Moral imperative: care close to home with free medicines and diagnostics for the poor; the welfare State's duty under Article 47 (public health among the State's primary duties).
- Precondition for development: the UN reaffirmed in 2019 that health is a precondition for sustainable development; primary care prevents costly hospitalisation; out-of-pocket share fell from 64.2 to 43.4 per cent with the Arogya Mandirs credited; a healthier workforce.
- Gaps: underfunded for chronic disease; a common prefix that blurred the mandates of sub-centres, primary and community health centres.
Conclusion: Conclude that without strong primary care, insurance only pays for illness that could have been prevented.
- UPSC Prelims 2023 Prelims-GSConsider the following statements :
- Statement-I : India's public sector health care system largely focuses on curative care with limited preventive, promotive and rehabilitative care.
- Statement-II : Under India's decentralized approach to health care delivery, the States are primarily responsible for organizing health services.
Which one of the following is correct in respect of the above statements?
How to approach this Prelims question
Approach: Step 1: Statement-I, a curative focus with limited preventive, promotive and rehabilitative care: correct. Step 2: Statement-II, the States are primarily responsible for organising health services: correct, health is in the State List. Step 3: does II explain I? No. Who runs health services does not decide what kind of care they give. So both correct, II not the explanation.
Trap to watch: Both statements are true and sound related, which tempts option (a).
Key facts to recall:
- (a) Both correct, II explains I: wrong. Being a State subject does not cause a curative focus.
- (b) Both correct, II does not explain I: right. Both are true, and they are about different things.
- (c) I correct, II incorrect: wrong. Entry 6 of the State List makes health a State subject.
- (d) I incorrect, II correct: wrong. Preventive care is a small share of spending, so I is correct.
Answer signal: Option (b), the official answer: both statements are correct and Statement-II is not the correct explanation for Statement-I.
Sources
- PIB: Update on Ayushman Bharat Pradhan Mantri Jan Arogya Yojana (28 March 2025)
- PIB: Transforming Healthcare, Six Years of Ayushman Bharat PM-JAY (23 September 2024)
- PIB: Cabinet approves health coverage to all senior citizens of the age 70 years and above (11 September 2024)
- PIB: Implementation of National Health Protection Scheme (Rajya Sabha reply)
- PIB: Beneficiaries under Ayushman Bharat PMJAY (7 December 2021)
- National Health Authority
- PIB: Ayushman Bharat Digital Mission marks a three-year journey (27 September 2024)
- Constitution of India, Seventh Schedule, List II (State List), Entry 6
- The Hindu, Delhi, 2 May 2026: Work in progress (editorial on the NSS 80th round health survey)
- The Hindu, Delhi, 5 and 11 May 2026: medical inflation and out-of-pocket expenditure; editorial on ESIC health check-ups
- The Hindu, Delhi, 12, 24 and 27 May 2026: Suvendu orders rollout of Central schemes in Bengal; Ayushman Bharat scheme to start in Bengal from July 1; the NSS 80th round on health
- The Hindu, Delhi, 28 and 29 May 2026: Over 7 lakh Ayushman Bharat cards issued in Delhi; Health expenses dip as govt. spend rises; National Health Accounts figures indicate high burden of health care costs
- The Hindu, Delhi, 21 June, 13, 18, 22 and 29 July 2026: J&K probe under PMJAY; Ayushman Divas; Delhi Arogya Mandirs; Rajasthan MAA Yojana portability; Ayushman cards in Parliament
- The Hindu, Delhi, 2, 3, 4 and 8 September and 1 October 2026: Bengal's health insurance; Private hospitals halt Ayushman services over unpaid dues; mental health cover; childbirth costs; Delhi Arogya Mandirs
- NCERT: Indian Constitution at Work (Class XI), Chapter 7, Federalism
- World Health Organization: Universal health coverage (fact sheet)
- Wikipedia: Ayushman Bharat Yojana
- UPSC: Civil Services Examination question papers
Editorial Disclaimer
This article draws on official releases of the Health Ministry, the Constitution and the other sources listed on this page.


